A claim is often rejected before anyone reviews the clinical value of the procedure. The operative note may describe an SI joint injection, while the claim uses a code intended for a nerve block. Or the provider performs an unguided injection but submits the image-guided code. For a pain and wellness clinic serving Chicago Ridge, Palos Heights, Palos Hills, Evergreen Park, and Hickory Hills, these distinctions affect payment, compliance, and the credibility of the entire billing record.
The right sacroiliac joint injection CPT code follows the procedure's anatomical target, imaging method, laterality, and documentation. Staff should never choose the code from the diagnosis alone. A patient may have sacroiliac joint pain, but the procedure could target the joint space or the nerves supplying it, and those are different coding pathways.
Table of Contents
- Introduction to Sacroiliac Joint Injection Coding
- Historical Context and Imaging Requirements
- Detailed Code Entries and Anatomical Targets
- Modifiers and Bilateral Procedure Rules
- Documentation Standards and Cross-References
- Common Coding Pitfalls and Compliance Risks
- Payer Considerations for Illinois Clinics
- Quick Reference Guide and Final Takeaways
Introduction to Sacroiliac Joint Injection Coding
Start with the anatomical target
Begin by reading the procedure note for one question: Where did the needle go?
If the provider placed the needle directly into the sacroiliac joint and confirmed intra-articular positioning with imaging, the primary Medicare code is CPT 27096. CMS describes 27096 as an injection into the sacroiliac joint with image guidance. The code is unilateral, so bilateral SI joint arthrography is reported with modifier 50 under CMS guidance, as documented in its Medicare billing article for SI joint injections.
If the provider targeted the nerves innervating the sacroiliac joint rather than the joint space, the correct code is CPT 64451. The diagnosis may still refer to SI joint pain, but the procedure is a nerve block, not an intra-articular injection. HHS OIG also distinguishes 27096 from 64451 by the procedure performed and states that Medicare payment depends on reporting the correct code, as shown in its audit summary on SI joint injection coding.
That distinction should be visible in the operative note, not inferred from a scheduling label or a charge description.
Build the claim from the note
A practical workflow has four checkpoints:
- Identify the target. Confirm whether the physician treated the joint space or the nerves.
- Confirm imaging. Determine whether fluoroscopy or CT documented the needle position.
- Check laterality. Match right, left, or bilateral treatment to the claim lines and modifier rules.
- Review the payer pathway. Medicare and commercial plans may apply different coverage and authorization requirements.
The diagnosis supports medical necessity, but it doesn't select the CPT code by itself. A useful clinical overview of sacroiliac joint pain treatment options can help staff understand the broader treatment context, while the operative note remains the controlling billing document.
Practical rule: Code the intervention that was performed, not the condition that brought the patient to the clinic.
For a clinic in Illinois, this discipline protects the revenue cycle without turning coding into guesswork. The biller should be able to trace every submitted line back to a specific sentence in the provider's documentation.
Historical Context and Imaging Requirements
The current framework makes more sense when viewed against the earlier reporting method. In 2012, CPT coding for SI joint injections moved from a split approach to a single primary procedure code, 27096. The older structure used 27096 together with separate radiology guidance codes such as 73542 or 77003. The 2012 CPT update deleted 73542 and removed references to 77003 and 77012 for this service, a transition documented in the CMS coding guidance for the SI joint injection code set.
Why the old split model causes trouble
New staff sometimes find historical claim examples in a practice system and assume the same combination remains appropriate. That approach can create duplicate or unsupported lines. The modern primary pathway centers on 27096 when the provider performs a directly injected, image-guided SI joint procedure and documents the intra-articular placement.
CMS guidance still distinguishes the procedure from ancillary imaging services. Fluoroscopic guidance may be associated with CPT 77003, and CT guidance may be associated with CPT 77012 when used to locate the needle insertion site, while formal arthrography can involve separate radiologic supervision and interpretation rules. Whether an ancillary service is separately reportable depends on the exact service and payer policy, so staff shouldn't automatically add an imaging line because a procedure used imaging. The applicable operational distinctions appear in CMS guidance on SI joint injection billing and imaging.
Imaging changes the coding pathway
For direct joint injections, imaging isn't a decorative detail. CMS states that 27096 should be used only when imaging confirms intra-articular needle placement. A note that says “injection performed” without recording the imaging method and confirmation leaves the claim vulnerable, even if the clinical service was appropriate.
The modality also matters because the claim must reflect the actual technique. A fluoroscopy-guided procedure and a CT-guided procedure may share the same primary SI joint code, but the documentation should identify which method guided the needle and how placement was verified. The clinic's fluoroscopy-guided injection information can support patient-facing education, but coding staff still need the physician's procedure-specific documentation.
The historical change simplified the primary code structure, but it didn't remove the need for precise records. It shifted responsibility toward matching one central procedure code with strong evidence of the target and imaging confirmation.
Detailed Code Entries and Anatomical Targets
A reliable code selection process starts with anatomy, not reimbursement assumptions. CPT 27096 and CPT 64451 can both appear in care for SI-related pain, but they describe different interventions. An unguided injection creates a separate pathway under Medicare guidance and shouldn't be forced into either image-dependent code.
The core code distinctions
| CPT Code | Anatomical Target | Imaging Requirement | Laterality |
|---|---|---|---|
| 27096 | Direct injection into the sacroiliac joint | Imaging must confirm intra-articular needle placement | Unilateral; bilateral reporting uses modifier 50 under CMS guidance |
| 64451 | Nerves innervating the sacroiliac joint | Follow the documented procedure and payer requirements for the nerve block | Report according to the documented side and payer rules |
| 20552 | Injection into a muscle or other specified structure pathway used for the applicable unguided SI injection situation | No CT or fluoroscopic guidance in the specific Medicare circumstance described below | One unit for unilateral or bilateral SI injection(s) under that guidance |
The table should be used as a decision aid, not as a substitute for reading the operative note. 27096 is not a generic SI pain code. It requires a direct joint injection with imaging confirmation. 64451 is not an alternative label for the same service. It applies when the provider targets the nerves that innervate the joint.
A note-based decision sequence
Ask these questions in order:
- Was the joint space entered? If yes, look at 27096, provided imaging confirmed intra-articular placement.
- Were the innervating nerves targeted? If yes, evaluate 64451.
- Was the SI injection performed without CT or fluoroscopic guidance? In the Medicare circumstance identified by CMS and its contractor guidance, don't submit 27096, 20610, or 20611. Use 20552, one unit, for unilateral or bilateral SI joint injection(s), when the stated patient conditions apply.
- Does the note support laterality and technique? If not, query the provider before submission.
CMS specifically identifies the unguided pathway for nonpregnant patients without contrast allergy when the injection is performed without CT or fluoroscopic guidance. The instruction is not a general license to use 20552 whenever imaging is missing. It applies to the defined Medicare scenario and should be checked against the relevant payer policy and patient record. Noridian's Medicare coding guidance for unguided sacroiliac joint injections provides the operational distinction.
A coder who chooses 27096 because the appointment was called an “SI injection” is taking a risk. The physician's documented target and imaging confirmation must control.
Modifiers and Bilateral Procedure Rules
Modifier work begins only after the base code is correct. A modifier can't repair a mismatch between an intra-articular injection and a nerve block, and it can't supply imaging documentation that the operative note lacks.
Reporting bilateral direct injections
CMS states that 27096 is unilateral. When the provider performs bilateral SI joint arthrography, CMS directs use of modifier 50. The claim should also make the bilateral service unmistakable in the procedure note, including the right and left targets and the imaging confirmation for each treated side.
A clean process looks like this:
- Verify both sides in the note. The physician should identify right and left treatment.
- Confirm the same procedure occurred on each side. Don't assume that a bilateral diagnosis means bilateral treatment.
- Apply modifier 50 to 27096 in accordance with the Medicare claim format and the payer's instructions.
- Check the claim edit. Make sure the units, line structure, and modifier align with the payer's bilateral billing rules.
- Retain the imaging record. The documentation should support needle placement on the treated sides.
Commercial plans may require a different line configuration or laterality convention. That doesn't override the CMS rule for Medicare, but it does mean staff should maintain payer-specific claim instructions rather than applying one template to every insurer.
Separating distinct services
Modifiers 59 and the X modifiers exist to identify distinct procedural services when the services are separately reportable and the documentation supports the separation. They shouldn't be used as a routine way to bypass a denial edit or unbundle services that belong together.
For example, a same-day nerve block and direct joint injection require careful review of the anatomical targets, sides, clinical purpose, and payer edits. If the provider's note doesn't clearly distinguish the procedures, the biller should query the provider instead of stacking modifiers. A modifier is an explanation of a documented circumstance, not a replacement for that circumstance.
Audit-safe habit: Apply the modifier after confirming the code, target, side, and distinct-service rationale. Never start with the modifier.
The same discipline prevents undercoding. If a bilateral direct injection is supported and the payer requires modifier 50, omitting it can distort the claim. If only one side was treated, adding it can create a different problem. Laterality must come from the procedure note, not from habit or scheduling data.
Documentation Standards and Cross-References
A defensible claim tells one continuous story. The clinical assessment identifies the suspected pain source, the procedure note identifies the target, the imaging record confirms technique, and the claim reports the matching code. If any link is vague, the billing team has to make an assumption, and assumptions create avoidable audit exposure.
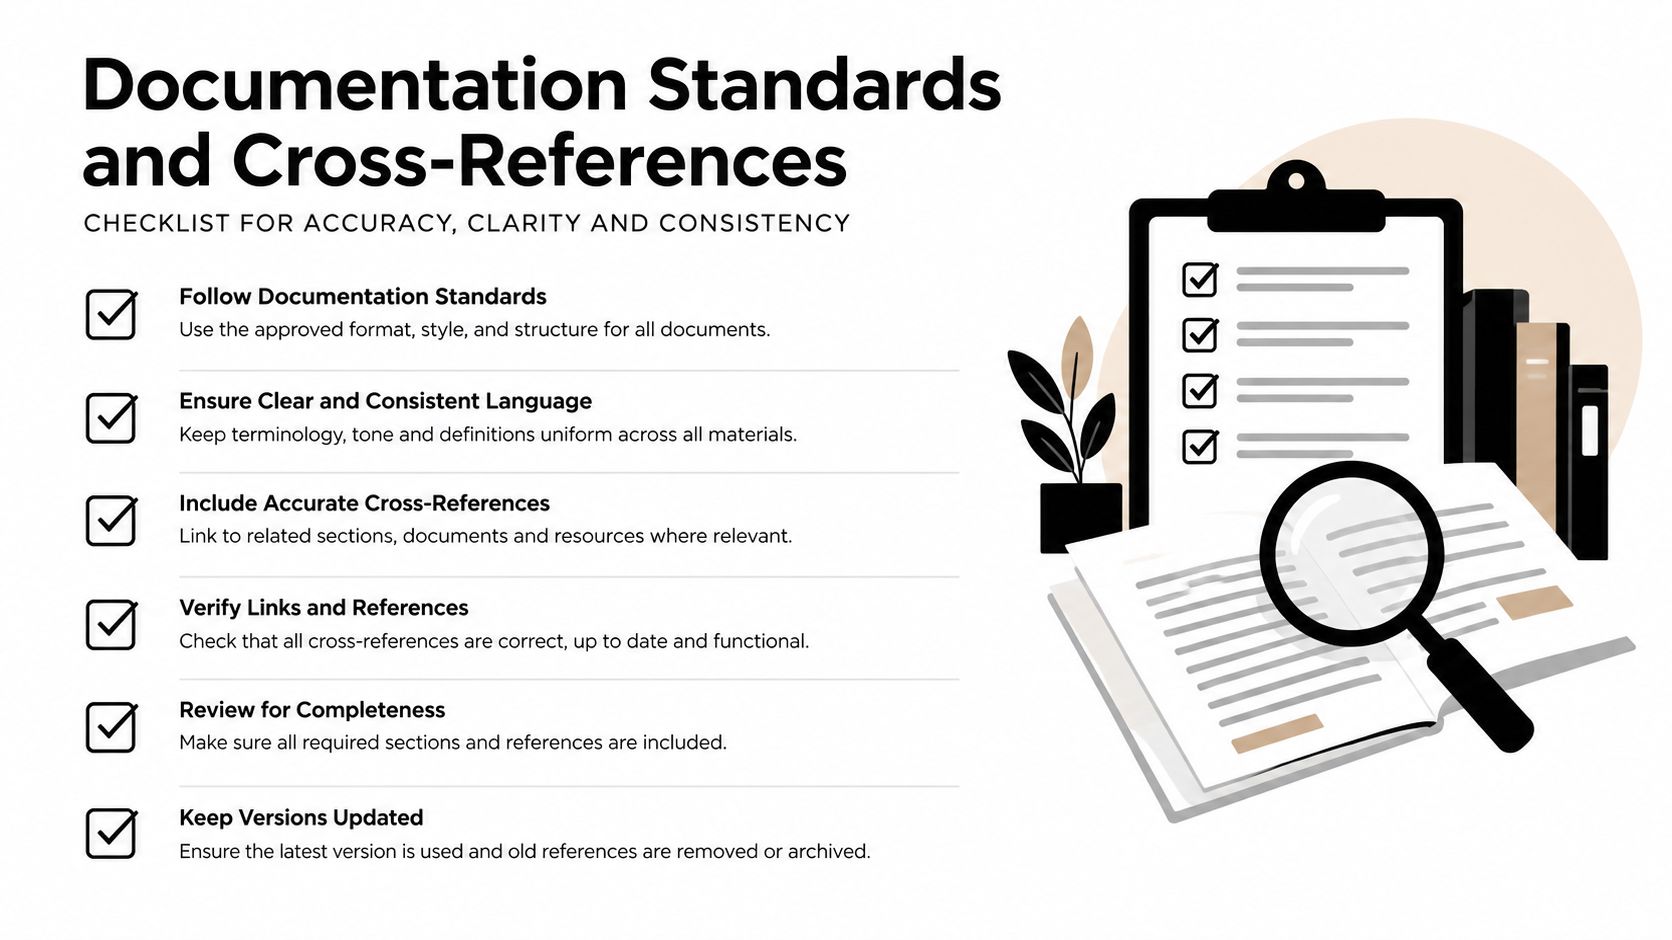
What the procedure note should establish
For a direct SI joint injection, the operative note should identify the treated side, the anatomical approach, the imaging modality, and the confirmation of intra-articular needle placement. If contrast was used, the note should describe the observed flow or other confirmation relevant to the procedure. The record should also identify the medication administered, the patient's response, complications if any, and post-procedure instructions.
For a nerve block, the note must instead identify the nerves targeted and distinguish that service from an injection into the joint space. Writing “SI injection” alone is too imprecise when the submitted code depends on whether the provider treated the joint or its innervation.
A useful internal checklist includes:
- Target: Joint space or innervating nerves.
- Laterality: Right, left, or bilateral.
- Guidance: CT, fluoroscopy, or no CT or fluoroscopic guidance.
- Placement: How imaging confirmed the intended position.
- Injectate: The substances and amounts used.
- Outcome: Immediate response, complications, and instructions.
Connect the note to the rest of the chart
The procedure note shouldn't stand alone. The assessment should explain why the intervention was considered, while the treatment plan should place the injection within the patient's broader opioid-sparing care. Coordination with targeted physical therapy, primary care, surgeons, chiropractors, or rehabilitation professionals can clarify how the procedure fits into functional recovery, but those related services don't change the SI injection CPT code.
E/M reporting also requires separation. If a same-day evaluation and management service is billed, the record must support a significant, separately identifiable service when the payer requires such documentation. The presence of a procedure doesn't automatically justify an additional E/M line, and an E/M code doesn't cure a weak procedure note.
Providers serving Palos Heights and Evergreen Park should train staff to read the complete encounter rather than copy forward a prior template. A prior note may describe a different target, side, or imaging method. Copying it into a new encounter can create contradictions that are more damaging than a simple omission.
Common Coding Pitfalls and Compliance Risks
The most persistent error is treating every SI-related procedure as interchangeable. It isn't. A direct injection into the joint, a nerve block, an injection performed without the required imaging, and a major-joint injection are different coding situations.
The major-joint substitution problem
CMS guidance says providers shouldn't substitute CPT 20610 or 20611 for SI joint injections. Those codes do not become appropriate just because the SI joint is a joint or because the provider used a familiar office injection template. The anatomical target and the applicable guidance determine the pathway.
The same warning applies to 27096. If the note doesn't establish image-confirmed intra-articular placement, the staff shouldn't submit 27096 and hope the diagnosis will carry the claim. CMS describes 27096 as an image-guided SI joint injection and limits its use to cases where imaging confirms the needle position.
Unguided procedures require a different review
An unguided injection may be clinically selected in a particular circumstance, but it shouldn't be billed as though CT or fluoroscopy occurred. CMS contractor guidance states that, for SI joint injections without CT or fluoroscopic guidance in nonpregnant patients without contrast allergy, providers shouldn't bill 27096, 20610, or 20611. The guidance directs use of 20552, one unit, for unilateral or bilateral SI joint injection(s).
That rule is narrow. Staff should verify the patient factors, the absence of the specified imaging, and the payer's current instructions before using the alternative pathway. If the record is silent about pregnancy status, contrast allergy, or imaging, the correct response is clarification, not automatic code substitution.
Denial prevention starts before charge entry. Ask what was injected, where the needle was placed, and how placement was confirmed.
Other frequent failures include missing laterality, unsupported bilateral reporting, duplicating imaging services, and using modifier 59 to force payment for services that aren't distinct. The procedure note should also make clear whether the intervention was directed at the joint or nerves. Staff who work with other interventional procedures can review the clinic's facet joint injection procedure information for broader procedural context, but the SI claim still requires its own target-specific documentation.
Payer Considerations for Illinois Clinics
A clinic in Illinois may treat patients from Chicago Ridge, Palos Hills, Hickory Hills, Palos Heights, and Evergreen Park, yet the payer's claim rules remain more important than the patient's city. Chicago Ridge is geographically close to Palos Hills and Palos Heights, which makes these practical nearby service-area targets, but proximity doesn't create one universal billing policy. Each plan still determines its authorization, documentation, claim-format, and reimbursement requirements.
Medicare dates matter
CMS coverage policy for SI joint injections is date-specific. Medicare LCD language states that coverage applies to services performed on or after March 19, 2023, and the record includes annual revisions in 2024 and 2025 marked “no changes,” as shown in the CMS Medicare coverage policy for SI joint injections.
That history matters operationally. A billing manual copied from an older period may not reflect the policy active on the date of service. Before submitting a Medicare claim, staff should verify the applicable LCD, the contractor instructions, and the patient's coverage status for the actual service date. Don't rely on a procedure label in the electronic health record or on a code set saved in a legacy charge table.
Build an Illinois payer workflow
A practical workflow for an Illinois pain clinic can separate universal clinical checks from payer-specific claim checks:
- Clinical review: Confirm target, laterality, imaging, placement, medication, and response.
- Coverage review: Check whether the plan requires authorization or has a procedure-specific policy.
- Claim review: Apply bilateral and distinct-service rules according to the payer's instructions.
- Record retention: Keep the operative note and imaging confirmation available for review.
Commercial insurers may not mirror Medicare's pathway. A plan may use different authorization rules, require a particular modifier arrangement, or apply its own policy to ancillary imaging. That variation makes a payer matrix useful, but the matrix should contain verified plan instructions rather than assumptions borrowed from another insurer.
For local practices, the strongest operational approach is simple: maintain a current Illinois payer reference, assign responsibility for policy updates, and require a pre-bill review when the procedure note doesn't clearly match the selected code. That process reduces avoidable rework without changing the clinical decision.
Quick Reference Guide and Final Takeaways
A daily reference should be short enough to use during charge review but precise enough to stop the common errors. The most important question remains anatomical: did the provider inject the joint, block the nerves, or perform an unguided injection that falls under a separate Medicare pathway?

Four checks before submission
- Match the target. Use 27096 for a direct, image-confirmed intra-articular SI joint injection. Use 64451 when the procedure targets the nerves innervating the joint.
- Match the imaging. Confirm that the note documents CT or fluoroscopic confirmation when 27096 is reported.
- Match the side. Verify right, left, or bilateral treatment. For bilateral 27096 reporting under CMS guidance, apply modifier 50.
- Match the payer. Check the active Medicare policy or commercial plan instructions for the date of service.
Five rules worth keeping beside the claim queue
- Don't substitute major-joint codes. CMS guidance rejects using 20610 or 20611 as substitutes for SI joint injections.
- Don't infer imaging. A scheduled fluoroscopy procedure isn't proof that fluoroscopic confirmation occurred.
- Don't confuse joint and nerve procedures. The diagnosis may be similar, but 27096 and 64451 represent different anatomical targets.
- Don't force a modifier. Modifier 59 or an X modifier requires a documented distinct service.
- Don't ignore the unguided pathway. In the specified Medicare situation involving a nonpregnant patient without contrast allergy, an SI injection performed without CT or fluoroscopic guidance follows the 20552, one-unit instruction rather than 27096.
The most useful internal habit is a pre-bill pause. Before the claim leaves the clinic, the biller should be able to point to the exact note language supporting the code, imaging requirement, laterality, and modifier. If that evidence isn't present, a provider query is safer than a guess.
Midwest Pain & Wellness offers image-guided sacroiliac joint injections as part of opioid-sparing pain care for patients with persistent low back or buttock pain. Visit Midwest Pain & Wellness to learn about evaluation and treatment options in the Chicago Ridge area, and contact the clinic to discuss whether an image-guided SI joint procedure fits your care plan.